
CLINICAL MEMORY
Longitudinal Metabolic Memory
Find 40+ prompt packs at templates.scribing.io to draft GLP-1 titration notes in seconds and surface unresolved BMI threshold or continuation questions.
Specialty Clinical Playbook
Structured GLP-1 documentation, BMI-indexed milestone tracking, and payer-ready prior-auth evidence built for metabolic medicine. Book your audit at https://cal.com/merryai/demo.
 Dr. Sarah Chen, MD
Specialty Architecture
Engineered to mirror the pacing, diagnostic frameworks, and prior-authorization documentation requirements of metabolic and anti-obesity medicine.
CLINICAL MEMORY
Find 40+ prompt packs at templates.scribing.io to draft GLP-1 titration notes in seconds and surface unresolved BMI threshold or continuation questions.
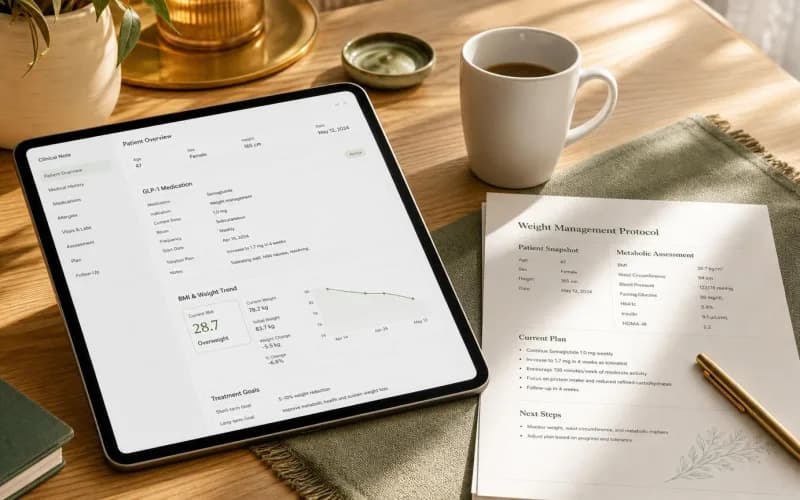
CONTEXT RETRIEVAL
Retrieve prior weight trajectories, A1c trends, baseline maximum weight, and lipid panels in one structured draft without tab bouncing.
WORKFLOW INTELLIGENCE
Capture longitudinal complexity add-on revenue for single serious or complex condition management and auto-draft care plans. Claim your 15-Minute Workflow Audit today.

SPECIALTY-AWARE REASONING
Diarize counseling dialogue and map BMI thresholds, comorbidities, prior trials, and lifestyle adherence into payer-approved prior-auth fields for clinician attestation.
Point-of-Care Flow
Zero IT friction, zero complex API setup, and human-verified attestation on every note and prior-authorization statement.

Clinical documentation in Endocrinology and medical weight management is uniquely burdened by longitudinal data density. A single follow-up encounter for a patient on semaglutide or tirzepatide must reconcile date-stamped weight, BMI, and waist circumference against a baseline maximum weight, a payer-recognized starting point, and a percentage total-body-weight-change calculation. Merry AI is architected to treat the chart not as a snapshot but as a continuous metabolic timeline, capturing each measurement with its source, timestamp, and calculation method.
Weight-management encounters demand structured intake that establishes obesity severity, overweight status where applicable, and the comorbidities that establish treatment necessity: type 2 diabetes, hypertension, dyslipidemia, obstructive sleep apnea, cardiovascular disease, and hepatic steatosis. Published Epic workflows describe medical assistants obtaining vitals, the system calculating BMI, and a standardized weight-history flowsheet being completed before the provider transitions into a dedicated obesity assessment. Merry AI mirrors this pacing, drafting into the same structured destinations rather than dumping unstructured narrative.
The distinction between calculation and clinical attestation governs the entire architecture. Merry AI may compute a BMI trend, identify a threshold crossing, or calculate percentage weight loss from a payer-recognized baseline, but the treating clinician must review the evidence, resolve any conflicting heights or weights, confirm medical necessity, and sign the submission. Every generated metric displays its underlying measurements, formula, dates, and source records so nothing is submitted as an opaque recommendation.
Baseline assessment in this specialty requires more granularity than most ambient scribes accommodate. Merry AI records height, weight, BMI with date and time, waist circumference when clinically relevant, weight trajectory including prior maximum weight, and the full ledger of prior interventions: diet, exercise, behavioral programs, and prior anti-obesity medications with duration and response. Relevant laboratory trends including A1c, fasting glucose, lipids, liver enzymes, renal function, and thyroid studies are pulled into the same timeline so trend interpretation is immediate.
Safety screening is documented as a first-class data element, not an afterthought. Contraindications, personal or family history of medullary thyroid carcinoma, pancreatitis history, gallbladder disease, pregnancy status where applicable, and relevant psychiatric or eating-disorder history are captured discretely. This structured safety layer feeds directly into the prior-authorization safety criteria field and into the clinician's attestation checklist before any GLP-1 order is finalized.
The following matrix demonstrates how Merry AI aligns a metabolic diagnostic framework with the discrete clinical data points required to defend both medical necessity and payer prior authorization. Each row represents a defensible link between what was documented and what a payer or auditor will demand.
| Specialty Diagnostic Framework | Required Clinical Data Points | Billing / PA Evidence |
|---|---|---|
| Obesity severity (BMI class I-III) | Date-stamped height, weight, BMI, threshold crossings | Met / missing / conflicting BMI vs payer threshold |
| Comorbidity-supported necessity | Active T2DM, HTN, dyslipidemia, OSA diagnoses + onset dates | ICD-10 linkage and supporting labs (A1c, lipids) |
| Lifestyle intervention requirement | Program name, duration, adherence, documented response | Met / incomplete for payer prerequisite |
| Prior anti-obesity medication trial | Drug, dose, duration, outcome, reason for discontinuation | Step-therapy evidence Met / incomplete |
| Weight-loss response / continuation | Baseline weight vs current; % total-body-weight change | Calculated ≥5% continuation threshold |
| Longitudinal complexity (focal point) | Continuity of care for single serious/complex condition | CPT G2211 add-on to 99202-99215 |
| Safety attestation | Contraindications, thyroid/pancreatitis history, labs | Drafted / unsigned pending clinician review |
Payer criteria are plan-specific and change over time, so Merry AI maintains versioned criteria carrying payer identity, effective date, drug and indication, and initial-versus-renewal distinctions. The system never represents an inferred checklist as an official payer requirement unless the requirement has been verified from an authoritative source. Clinicians should always confirm coding and coverage against the current CMS guidance at https://www.cms.gov/medicare/coding-billing/icd-10-codes before submission.
Milestone tracking is where longitudinal memory becomes payer-ready evidence. Merry AI explicitly surfaces the encounter when BMI first exceeded a payer threshold, the baseline BMI at treatment initiation, six- and twelve-month weight-response milestones, percentage weight loss from the recognized baseline, and any weight regain or inadequate response. Each milestone carries its source, timestamp, calculation method, and a confidence status, because payer reviewers routinely reject evidence that is undated, internally inconsistent, or drawn from an unverified free-text note.
Continuation and renewal authorizations are treated as distinct workflows from initial submissions. When a patient reaches a maintenance phase, the system recalculates cumulative percentage loss, flags tolerability signals from prior visits, and drafts the continuation-criteria statement for clinician attestation. This closes the gap that most documentation tools ignore, where initial approval is captured but the renewal evidence evaporates into scattered progress notes.
Deployment inside AthenaOne and Epic occurs through a Chrome Extension that performs DOM injection into the clinician's active browser session. There is no HL7 interface build, no FHIR endpoint provisioning, and no marketplace approval queue. The finalized obesity and endocrine note flows into HPI, physical exam, assessment/plan, and social history sections of the open chart with a single click, preserving the EHR's native audit trail and user attribution exactly as if the clinician had typed it.
This user-mediated architecture is a deliberate compliance choice. Because Merry AI organizes verified data into a clinician-reviewable evidence matrix rather than autonomously determining medical necessity or auto-submitting attestations, it aligns with lower-risk clinical decision-support principles. The clinician remains the decision-maker who reviews the surfaced measurements, resolves discrepancies, and signs. Explore the full library of specialty prompts to accelerate this workflow — Access Specialty Prompts at templates.scribing.io.
Documentation integrity is non-negotiable in a specialty where AI-generated text could otherwise introduce unsupported diagnoses, fabricated treatment failures, or inaccurate dates. Merry AI's audit trail records which evidence was automatically retrieved, which calculations were generated, what the clinician changed, and who signed the final submission. Original clinical data and AI-generated content remain clearly separated, satisfying both information-blocking expectations and internal coding-compliance review.
Protected Health Information is processed under a zero-retention model with RAM-based transient handling and shredding on note finalization, governed by an executed Business Associate Agreement, role-based minimum-necessary access, encryption in transit and at rest, and explicit contractual prohibition on repurposing identifiable clinical data for general-purpose model training. For departments ready to validate extraction precision, calculation accuracy, and PA completeness against real patient timelines, Schedule a 15-Minute Specialty Workflow Audit and we will demonstrate the evidence matrix on a controlled multi-year weight-management case.

Convert dietetic assessments into clinician-reviewed ADIME drafts with transparent G0270 unit logic. Book your audit at https://cal.com/merryai/demo.

Convert member priorities and verified data into traceable, clinician-reviewed longitudinal summaries and care-goal records. Book your audit at https://cal.com/merryai/demo.

Merry AI assembles payer-defensible six-month medical-necessity packets with source-linked provenance and surgeon attestation. Book your audit at https://cal.com/merryai/demo.